Menopause Hair Thinning — A Physician's Guide to Drug-Free Recovery
Part of: Women's Hair Loss — A Physician's Clinical Knowledge Center
By Dr. Susan Lin, M.D. — Board-Certified OB/GYN & Anti-Aging Medicine Physician. Reviewed: May 2026.
The short answer
Menopause-related hair thinning is common: in a cross-sectional study published in Menopause, just over half of postmenopausal women (52.2%) showed female-pattern hair loss (Chaikittisilpa et al., 2022). Unlike postpartum shedding (acute and self-limited), menopause thinning is gradual, diffuse, and progressive — driven by declining estrogen combined with a relative rise in scalp follicle sensitivity to DHT. Most women notice the first signs in their early-to-mid 40s during perimenopause, with thinning often accelerating around the final menstrual period. The good news: menopause thinning is highly responsive to sustained, non-prescription intervention — and most women see meaningful improvement in density within 3 to 6 months.
Why it happens — the biology
Throughout reproductive years, estrogen acts as a protective hair signal: it prolongs anagen (growth phase) and dampens scalp sensitivity to DHT. By menopause, estrogen falls to a small fraction of premenopausal levels. Three things happen at the follicle:
- Anagen shortens — hairs spend less time growing, ending up shorter and thinner
- Telogen ratio rises — more hairs in the shedding phase at any moment
- Relative DHT sensitivity increases — without estrogen's protection, follicles miniaturize over time
Visible result: gradual but progressive thinning at the part line, crown, and overall scalp density — with frontal hairline typically preserved.
The realistic timeline
| Life phase | Typical age | What's happening |
|---|---|---|
| Late 30s | 35-40 | Subtle anagen shortening |
| Early perimenopause | 40-45 | Strands feel finer; mild density reduction |
| Late perimenopause | 45-50 | Diffuse thinning; widening part; visible scalp at crown |
| Around final menstrual period | 49-52 avg | Acceleration of thinning over 1-2 years |
| Postmenopause | 50+ | Continued thinning if untreated; often stabilizes with intervention |
The non-prescription recovery framework
Because the dominant mechanism is DHT sensitivity, the framework emphasizes botanical and nutritional follicle support.
1. Inside-out botanical support
MD Nutri Hair delivers a clinical dose of Lilac extract titrated for verbascoside alongside marine collagen, biotin, flaxseed lignans, and vitamin E. The single highest-leverage intervention in my menopause framework. Drug-free — no minoxidil, no finasteride — and no interaction with HRT.
2. Topical scalp environment with peptides and saw palmetto
MD Follicle Energizer combines saw palmetto with Biotinoyl Tripeptide-1. MD Revitalizing Treatment Shampoo and Conditioner with StimuCap® peptide technology support scalp microcirculation. Sulfate-free and drug-free.
3. The MD Hair Restoration Kit — full system for menopause
The MD Hair Restoration Kit combines scalp serum + topical activator + oral supplement into a coordinated 3-step protocol — the system I most often recommend to menopause patients because it addresses scalp environment + botanical follicle support + nutritional support simultaneously.
4. Nutritional foundation with menopause emphasis
- Ferritin >70 ng/mL
- Vitamin D 30-60 ng/mL
- Protein 1.0-1.2 g/kg body weight daily
- Omega-3 fatty acids for scalp inflammation
- Calcium and vitamin K2 (bone health priority)
5. Sleep, stress, and exercise
Menopause sleep disruption compounds hair stress. Treating insomnia and night sweats — lifestyle, HRT (if appropriate), or non-hormonal options — supports the hair growth cycle. Regular resistance exercise supports hormonal milieu and bone density.
What about HRT?
HRT may help some women experience improvement in hair density because it restores some estrogenic protection at the follicle. The effect is variable. HRT does not replace the non-prescription framework — even women on HRT benefit from nutritional support, botanical follicle support, and gentle scalp care. The core MD® Hair lineup — MD Nutri Hair™, MD® Follicle Energizer, MD® Scalp Essential, and the MD® Revitalizing Treatment Shampoo & Conditioner — is drug-free (no minoxidil, no finasteride, no prostaglandin compounds) and can be safely combined with any HRT regimen. HRT decisions should be individualized with your physician.
When menopause hair thinning warrants evaluation
- Sudden severe shedding rather than gradual onset
- Focal patches of complete baldness (suggests alopecia areata)
- Scalp pain, burning, scaling, or redness
- Eyebrow thinning, fatigue, cold intolerance (suggests thyroid disease — very common at menopause)
- Hirsutism, acne, or oily skin alongside hair thinning (may suggest androgen excess or PCOS)
Basic labs at menopause: CBC, ferritin, TSH, free T4, vitamin D, B12, FSH, estradiol, total and free testosterone, DHEA-S, fasting metabolic panel.
Frequently asked questions
Q: At what age does menopause hair thinning start?
A: Most women notice first signs in their early-to-mid 40s during perimenopause, accelerating around the final menstrual period (average age 51 in the US).
Q: Is menopause hair thinning permanent?
A: Without intervention, it is typically progressive. With consistent non-prescription intervention, most women see meaningful improvement within 3-6 months.
Q: Can I take MD Nutri Hair if I am on HRT?
A: Yes. MD Nutri Hair is drug-free (no minoxidil, no finasteride) with no known interactions. Discuss with your prescribing physician.
Q: Does HRT prevent menopause hair thinning?
A: HRT can help some women, but the effect is variable. The non-prescription framework is effective with or without HRT.
Q: How long until I see results from the MD Hair Restoration Kit?
A: Less shedding within 4-6 weeks; visible changes in density typically by 3-6 months.
Q: Is menopause hair thinning the same as female pattern hair loss?
A: They overlap significantly. Menopause often unmasks or accelerates genetic female pattern hair loss in susceptible women.
Bottom line
Menopause hair thinning is real, biologically driven, and common — but it is not untreatable. Combine nutritional repletion, scalp environment support, natural DHT modulation, stress and sleep optimization, and consistency over 3-6 months minimum. Earlier intervention preserves more existing follicle density.
Related reading
Featured products
Cited literature
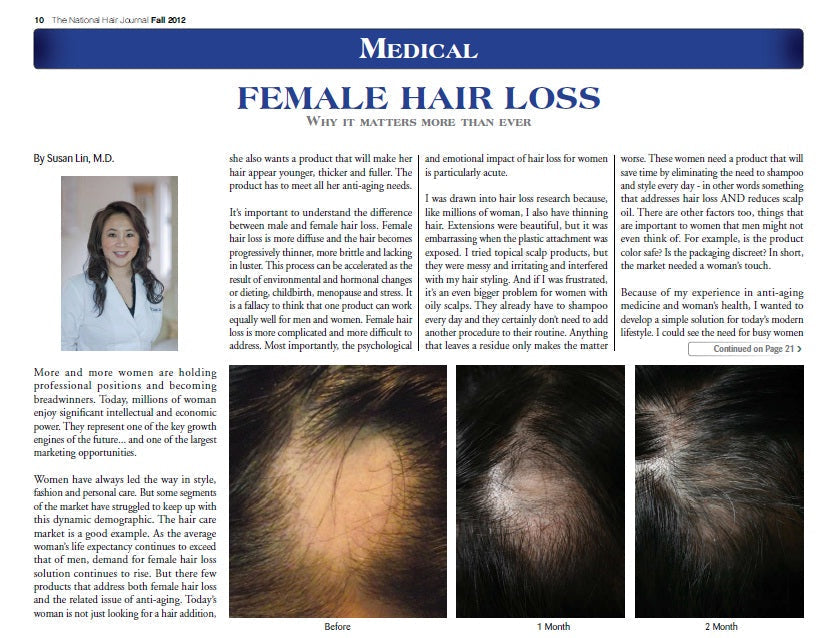
- Lin, S. F. (Fall 2012). Medical Female Hair Loss. The National Hair & Skin Journal, 16(63), 10–11. — Dr. Lin's published clinical framework for female hair loss.
- Lin, S. F. (April 2017). Novel Drug-Free Hair Loss Treatment. Euro Cosmetics. — Lilac verbascoside, DHT pathway modulation, and the rationale for non-prescription hair loss support.
- Lin, S. F. (2013). Stem Cells: The Recent Innovation in Hair Regeneration. The Link — The Voice of the American Hair Loss Council, Issue 7, p. 5.
- Mirmirani P. Hormonal changes in menopause. Br J Dermatol. 2011;165(s3):7-11.
- Almohanna HM et al. The role of vitamins and minerals in hair loss. Dermatol Ther. 2019;9(1):51-70.
Educational only; not a substitute for individualized medical advice.